
Sun, Oct 4, 2026

Volume 20, Issue 3 (May-Jun 2026)
mljgoums 2026, 20(3): 24-28 |
Back to browse issues page


Download citation:
BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:


BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:
Sheybani P, Nazarzadeh A, Keramati M R, Shams S F. The importance of blood products reservation management in tertiary hospitals: A case study from a tertiary educational hospital in the North East of Iran. mljgoums 2026; 20 (3) :24-28
URL: http://mlj.goums.ac.ir/article-1-1985-en.html
URL: http://mlj.goums.ac.ir/article-1-1985-en.html


1- Cancer Molecular Pathology Research Center, Mashhad University of Medical Sciences, Mashhad, Iran; Department of Hematology and Blood Banking, Faculty of Medicine, Mashhad University of Medical Sciences, Mashhad, Iran
2- Cancer Molecular Pathology Research Center, Mashhad University of Medical Sciences, Mashhad, Iran; Department of Hematology and Blood Banking, Faculty of Medicine, Mashhad University of Medical Sciences, Mashhad, Iran ,shamsf@mums.ac.ir
2- Cancer Molecular Pathology Research Center, Mashhad University of Medical Sciences, Mashhad, Iran; Department of Hematology and Blood Banking, Faculty of Medicine, Mashhad University of Medical Sciences, Mashhad, Iran ,
Full-Text [PDF 564 kb]
(1555 Downloads)
| Abstract (HTML) (7133 Views)
There was a gradual decline over the three years, representing a cumulative 16.5% reduction. This downward trend suggests some degree of systemic improvement or optimization in blood product use and request justification. However, the relative stability in the distribution of causes warrants closer examination of the individual categories to understand persistent challenges, which are discussed further below (Figure 5).
Other notable but less prevalent causes included adverse reactions. General non-use similarly showed a decreasing trend. Additional categories, such as mistakes in request, blood group mismatch, and surgery-related reasons, remained consistently low in frequency but are clinically significant because of their preventable nature. Mistakes in request increased slightly in the third year, suggesting minor variability but no systemic deterioration. Similarly, blood group mismatch remained rare but was present each year.
Discussion
Over three years at Imam Reza Hospital, the number of returned blood products steadily declined, suggesting improvements in utilization and systemic efficiency. However, the return percentage relative to total issued units did not consistently decrease; the final year even showed a slight increase, indicating unresolved inefficiencies in some departments.
Among clinical units, the Hematology-Oncology ward had the highest volume of returns, which was expected because of frequent transfusions in immunocompromised patients. The ICU and Emergency Department also had high return volumes. However, the Neurology ward showed the highest return percentage, reflecting inefficiency likely related to unclear transfusion protocols. Pediatric Cardiology and Gynecology also had elevated return percentages, possibly related to over-ordering for elective procedures. These findings indicate the need for targeted training and stricter ordering policies in specific departments.
By product type, platelets were most frequently returned in absolute numbers, followed by red blood cells (RBCs), fresh frozen plasma (FFP), and cryoprecipitate. However, FFP had the highest return rate, suggesting frequent precautionary ordering without subsequent transfusion. Platelets, because of their short shelf life, were often returned due to delays or cancellations. RBCs, although most frequently ordered, had relatively better utilization, likely due to controls such as Maximum Surgical Blood Ordering Schedules (MSBOS) and crossmatching protocols (1,3). In contrast, plasma and platelets lack such robust oversight, making them prone to overuse and waste (4,8).
Patient Blood Management (PBM), endorsed by international bodies such as the AABB, offers an evidence-based solution to transfusion inefficiencies. PBM reduces unnecessary transfusions and improves patient outcomes (9-11). It also emphasizes interprofessional collaboration between clinical and laboratory staff (12,13). While RBC use is often audited using the crossmatch-to-transfusion (C/T) ratio (14), plasma and platelets lack parallel tools. Introducing metrics such as transfusion trigger compliance, post-transfusion effectiveness, and return rate audits can extend PBM principles to all blood components.
Improper handling of returned units also contributes to wastage (15). For example, refrigerating platelets-which should be stored at room temperature with agitation (16,17)-renders them unusable. Such errors, often due to inadequate training, make products ineligible for reissue (18,19). Preventing these errors requires staff education on proper storage, clear return protocols, and limiting unnecessary issue of products in the first place.
When reasons for return were analyzed, the most common cause was “Physician Decision / Order Canceled,” which was often linked to last-minute clinical changes without timely notification of the blood bank. Elective surgeries were frequently postponed or canceled without informing transfusion services. These lapses lead to avoidable product returns and highlight the need for better coordination (5,6).
In teaching hospitals, these issues are magnified by the presence of rotating trainees. Inconsistent ordering habits and insufficient documentation by residents can cause systemic inefficiencies. Reinforcing documentation standards, improving communication, and enhancing supervision can reduce such preventable errors (5,15).
Another common reason for returns was “Patient Death,” which slightly increased over the study period. Although some of these cases are unavoidable, many reflect premature ordering for critically ill patients with poor prognoses. Multidisciplinary planning, especially in palliative cases, can reduce such waste.
Less frequent but serious return causes included “Mistakes in Request” and “Blood Group Mismatch.” Although rare, they indicate critical protocol failures. Preventing these errors requires comprehensive staff training, system-based safeguards such as LIS alerts, and double-checking mechanisms (4).
To address these challenges, hospital-wide digital interventions are essential. Tools such as transfusion order alerts, mandatory return documentation, and real-time dashboards can enhance accountability. Assigning clear responsibility for each transfusion order, alongside regular audits, promotes compliance and reduces waste.
Our findings also provide a valuable perspective on blood product management within Iran, revealing significant regional variation. The overall return percentage in our hospital, which fluctuated between 1.1% and 1.5%, compares very favorably with other published reports. For instance, a study in Qazvin province hospitals found an average wastage rate of 9.8% for all blood products, with packed red cell wastage in individual hospitals ranging from 1.93% to as high as 30.7% (20). This contrasts sharply with our results, as does an earlier report from Kerman province, which also noted alarmingly high return rates of up to 25% for certain products (2). The significant difference suggests that although our institution has its own inefficiencies, its baseline blood management protocols may be more effective than those in other domestic centers. This highlights considerable variability in transfusion practices across the country and underscores the urgent need for standardized, national-level guidelines to reduce waste.
These challenges related to variability and inefficiency are not unique to Iran; similar studies in other teaching hospitals worldwide have also linked higher wastage to inexperience among trainees and the absence of real-time data tracking or feedback. For example, Taichung Tzu-Chi Hospital in Taiwan-an academic medical center-found that a significant portion of wastage was caused by excessive or inappropriate orders and staff unfamiliarity with transfusion procedures, emphasizing the need for better education and monitoring systems (15). Similarly, UCSF-affiliated hospitals in the U.S. reduced inefficiencies by using web-based dashboards to monitor blood inventory and cooler status in real time (21). Our findings also identify platelets and plasma as the most frequently wasted products. At the University of Maryland Medical Center, R-based dashboards enabled rapid adjustments in transfusion volumes during COVID-19 (4). In contrast, our retrospective, manual approach lacks predictive tools and real-time oversight.
Emerging technologies such as artificial intelligence (AI) and machine learning present promising solutions. These tools can forecast demand, flag high-risk return scenarios, and optimize inventory using historical and real-time data (22). Studies show that AI can improve the C/T ratio, reduce inventory needs, and lower wastage without affecting patient care (23,24). Predictive systems could even warn clinicians when an order is unlikely to be used, supporting smarter stewardship practices.
By delineating these issues in detail, we propose a foundation for strategic interventions that are both feasible and impactful. Key among these is the development of demand-prediction models based on statistical forecasting for plasma and platelets, moving beyond reliance on traditional MSBOS-style templates. Regular education and training on transfusion practices, with emphasis on the appropriate storage and handling of returned units, are also essential. Moreover, strengthening accountability through mandatory documentation and clear communication for each returned unit-alongside follow-up by transfusion medicine personnel-can help mitigate waste. To enhance oversight, we recommend implementing digital dashboards to monitor real-time blood usage trends and trigger audits in high-return departments. Finally, the adoption of predictive technologies such as AI and machine learning can assist in accurately forecasting product needs and guiding order volumes, particularly in smaller or resource-limited hospitals.
Moving forward, prospective studies and implementation trials will be essential to validate these strategies and support their integration into hospital-wide blood management programs. Strengthening transfusion accountability, particularly within educational institutions, has the potential to significantly reduce blood product wastage while improving patient care and safety.
Conclusion
Although progress has been made in reducing total returns at Imam Reza Hospital, significant challenges remain, particularly due to its educational environment, lack of digital tools, and frequent misuse or mishandling of returned products. Unlike centers that employ real-time analytics and AI-based forecasting, our institution relies on delayed manual audits. Future efforts must focus on minimizing both the rate and risk of returns by integrating technology, standardizing protocols, and fostering a culture of accountability. With these changes, we can better preserve our limited blood resources and improve patient safety.
Acknowledgement
The authors would like to thank Mr. Rasoul Zare for data collection assistance.
Funding Sources
This study was supported by Mashhad University of Medical Sciences.
Ethical Statement
The study protocol was approved by the Ethics Committee of Mashhad University of Medical Sciences (Approval code = IR.MUMS.IRH.REC.1403.244).
Conflicts of Interest
The authors declared no conflict of interest.
Author Contributions
All authors contributed to the study design, data analysis, and interpretation. All authors participated in drafting and writing the manuscript. Parsa Sheybani and Ata Nazarzadeh contributed equally as first authors. All authors read and approved the final manuscript.
Data Availability Statement
The data that support the findings of this study are available from the corresponding author upon reasonable request. The data are not publicly available due to ethical restrictions and patient privacy regulations.
Use of Artificial Intelligence
As the authors are non-native English speakers, Gemini (Google) was used during the preparation of this manuscript solely to assist with language editing, text structuring, and formatting to improve readability.
The AI tool was not used for systematic search strategies, data extraction, statistical analysis, or the generation of scientific conclusions. Following the use of this tool, all authors thoroughly reviewed, edited, and validated the content, and assume full responsibility for the accuracy, originality, and integrity of the final published article.
Full-Text: (344 Views)
Introduction
Blood products are a critical component of modern hospital care and are regularly used in surgical procedures, emergency interventions, and chronic disease management (1). Since blood donation is voluntary and inherently limited, the wastage of any unit not only imposes financial strain on the healthcare system but also represents a lost opportunity to treat a patient in need (2). To ensure appropriate stewardship of this vital resource, the World Health Organization and national transfusion services emphasize the importance of evidence-based and efficient utilization of blood components (Clinical Transfusion Practice - WHO, 2021).
Despite global advancements, blood component wastage remains a persistent issue. In countries such as the United States and South Korea, red blood cell (RBC) discard rates have ranged from less than 1% to over 20%, depending on institutional policies, clinical workflows, and logistical practices (1,3). Rising costs associated with blood collection, testing, and storage further emphasize the urgency of minimizing unnecessary returns and discards (4). In Iran, studies have reported alarmingly high return and discard rates for blood components, with some centers showing return percentages as high as 25% for certain products, underscoring the urgent need for local interventions to improve blood utilization (2).
Several factors contribute to blood wastage in hospitals. These include excessive preoperative ordering, sudden procedure cancellations, transport-related handling errors, and failure to initiate transfusions within recommended timeframes (1). For instance, the commonly applied “30-minute rule,” which requires transfusion of RBC units within 30 minutes of issue, is often applied inconsistently, leading to unnecessary discards (5). In addition, insufficient cold-chain infrastructure and the lack of real-time monitoring systems contribute to high wastage, particularly in general wards and operating rooms (1). During the COVID-19 pandemic, institutions equipped with flexible, data-driven monitoring systems were better able to adjust transfusion practices in real time and reduce unnecessary waste (4).
To mitigate these inefficiencies, multiple interventions have been proposed. These include the use of temperature-sensitive indicators (TSIs) to monitor blood storage (5), implementation of digital alert systems, targeted staff education on transfusion safety, and hospital-wide Patient Blood Management (PBM) programs (6). Some countries have revised transfusion regulations-extending the 30-minute limit to 60 minutes based on evidence that product quality remains intact-which has significantly reduced discard rates (7). In Iran, assigning tariffs to blood products has been shown to improve clinician accountability and decrease unwarranted ordering (2).
Despite the availability of these strategies, localized analyses remain essential to identify context-specific inefficiencies. Therefore, this study aims to evaluate the patterns, causes, and departmental distribution of returned blood products over a three-year period at a major tertiary educational hospital in Iran. We hypothesize that the high rate of returned blood components is primarily driven by modifiable factors, including inadequate documentation, lack of real-time monitoring, and improper storage or cancellation protocols. By identifying department-specific and product-specific patterns, we aim to uncover opportunities for targeted interventions that can reduce unnecessary returns and optimize blood product utilization.
Methods
This retrospective cross-sectional study was carried out at Imam Reza Hospital, Mashhad, one of the largest educational hospitals in northeast Iran, with the objective of investigating the causes of non-utilization of reserved blood products. The study covered the period from March 2022 to March 2025.
Data were collected exclusively through a review of the hospital’s Laboratory Information System (LIS) and the digital dashboard used by the hospital blood bank. These systems provided access to detailed records of all blood products reserved during the study period, including RBCs, plasma, platelets, and cryoprecipitate. Each record included information such as the requesting department, product type and quantity, date of reservation, and whether the product was eventually used or returned.
The analysis focused on five primary clinical departments: Internal Medicine, Obstetrics and Gynecology, Surgical Wards and Operating Departments, Orthopedics, and Chemotherapy/Oncology. For each department, the rate of product utilization versus non-utilization was calculated. Additional parameters, such as the interval between reservation and return, reasons for expiry, and frequency of cancellations, were also assessed. Because some return entries lacked documented reasons, these cases were excluded from detailed cause-specific analyses. The study focused on returns with available documentation to better understand modifiable contributors to blood product wastage.
All data were organized into structured formats and analyzed using Microsoft Excel. Descriptive statistical methods were applied to identify trends and recurring issues related to over-reservation or logistical delays, with the ultimate goal of informing improved blood product management and reducing wastage.
The study protocol received ethical approval from the Ethics Committee of Mashhad University of Medical Sciences under the approval code IR.MUMS.IRH.REC.1403.244.
Results
Description of variables
The dataset comprises retrospective data on blood product orders that were not transfused, collected over three years (March 2022-2025). The primary variables assessed were the number of returned products, defined as the absolute count of blood components delivered but not transfused, and the return percentage, calculated as the number of returns divided by the total number of units delivered and expressed as a percentage. These indicators were stratified by both hospital section (Ward) and blood product type, allowing multidimensional evaluation of return patterns.
Trends across the three-year period
Analysis of temporal trends revealed a progressive decline in the total number of returned units over the three years studied. However, this trend was not entirely linear, as a modest increase to 1.3% was observed from March 2024 to March 2025 (Figure 1).
Analysis of hospital sections revealed substantial variation in both the frequency and rate of returns. In terms of absolute return counts, the Hematology-Oncology ward reported the highest number of returns, followed closely by the Intensive Care Unit (ICU), the Emergency Department, and the Internal Medicine ward. These departments collectively accounted for the majority of returned blood components over the study period. When the average return percentage was examined by department, notable differences emerged. The Neurology ward showed the highest mean return rate, followed by Pediatric Cardiology and Gynecology. Hematology-Oncology, despite having the highest number of returns, demonstrated a relatively low average return percentage, suggesting that its high return volume may be attributable to its overall high transfusion activity (Figure 2).
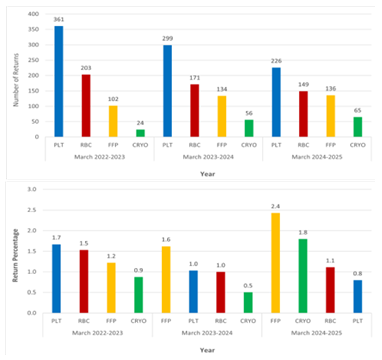
At the level of blood product types, four major categories were analyzed: red blood cell (RBC) units, platelets (PLT), fresh frozen plasma (FFP), and cryoprecipitate (CRYO). Among these, platelets accounted for the highest total number of returns, followed by RBC units, FFP, and CRYO. When expressed as average return percentages across all three years, FFP had the highest return rate (Figure 3). These findings indicate that, although PLT units were most frequently returned in absolute terms, FFP had the highest relative return rate.
When evaluated by product type over the three-year span, PLT units consistently showed the highest return volumes. Although CRYO and FFP had lower absolute return numbers, their return percentages-particularly for FFP-remained comparatively elevated (Figure 4).
|
Overview
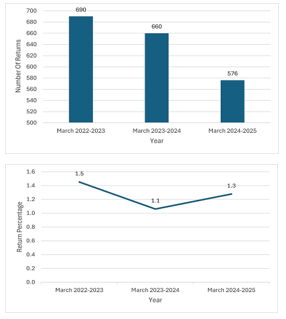 Figure 1. Number of returns (Left) and return percentage (Right) over the course of 3 years  Figure 2. Blood product return percentage (Top) and numbers (Bottom) by year and department  Figure 3. Overview of blood product returns (Right) and return percentage (Left) over the course of 3 years |
There was a gradual decline over the three years, representing a cumulative 16.5% reduction. This downward trend suggests some degree of systemic improvement or optimization in blood product use and request justification. However, the relative stability in the distribution of causes warrants closer examination of the individual categories to understand persistent challenges, which are discussed further below (Figure 5).

Other notable but less prevalent causes included adverse reactions. General non-use similarly showed a decreasing trend. Additional categories, such as mistakes in request, blood group mismatch, and surgery-related reasons, remained consistently low in frequency but are clinically significant because of their preventable nature. Mistakes in request increased slightly in the third year, suggesting minor variability but no systemic deterioration. Similarly, blood group mismatch remained rare but was present each year.
Discussion
Over three years at Imam Reza Hospital, the number of returned blood products steadily declined, suggesting improvements in utilization and systemic efficiency. However, the return percentage relative to total issued units did not consistently decrease; the final year even showed a slight increase, indicating unresolved inefficiencies in some departments.
Among clinical units, the Hematology-Oncology ward had the highest volume of returns, which was expected because of frequent transfusions in immunocompromised patients. The ICU and Emergency Department also had high return volumes. However, the Neurology ward showed the highest return percentage, reflecting inefficiency likely related to unclear transfusion protocols. Pediatric Cardiology and Gynecology also had elevated return percentages, possibly related to over-ordering for elective procedures. These findings indicate the need for targeted training and stricter ordering policies in specific departments.
By product type, platelets were most frequently returned in absolute numbers, followed by red blood cells (RBCs), fresh frozen plasma (FFP), and cryoprecipitate. However, FFP had the highest return rate, suggesting frequent precautionary ordering without subsequent transfusion. Platelets, because of their short shelf life, were often returned due to delays or cancellations. RBCs, although most frequently ordered, had relatively better utilization, likely due to controls such as Maximum Surgical Blood Ordering Schedules (MSBOS) and crossmatching protocols (1,3). In contrast, plasma and platelets lack such robust oversight, making them prone to overuse and waste (4,8).
Patient Blood Management (PBM), endorsed by international bodies such as the AABB, offers an evidence-based solution to transfusion inefficiencies. PBM reduces unnecessary transfusions and improves patient outcomes (9-11). It also emphasizes interprofessional collaboration between clinical and laboratory staff (12,13). While RBC use is often audited using the crossmatch-to-transfusion (C/T) ratio (14), plasma and platelets lack parallel tools. Introducing metrics such as transfusion trigger compliance, post-transfusion effectiveness, and return rate audits can extend PBM principles to all blood components.
Improper handling of returned units also contributes to wastage (15). For example, refrigerating platelets-which should be stored at room temperature with agitation (16,17)-renders them unusable. Such errors, often due to inadequate training, make products ineligible for reissue (18,19). Preventing these errors requires staff education on proper storage, clear return protocols, and limiting unnecessary issue of products in the first place.
When reasons for return were analyzed, the most common cause was “Physician Decision / Order Canceled,” which was often linked to last-minute clinical changes without timely notification of the blood bank. Elective surgeries were frequently postponed or canceled without informing transfusion services. These lapses lead to avoidable product returns and highlight the need for better coordination (5,6).
In teaching hospitals, these issues are magnified by the presence of rotating trainees. Inconsistent ordering habits and insufficient documentation by residents can cause systemic inefficiencies. Reinforcing documentation standards, improving communication, and enhancing supervision can reduce such preventable errors (5,15).
Another common reason for returns was “Patient Death,” which slightly increased over the study period. Although some of these cases are unavoidable, many reflect premature ordering for critically ill patients with poor prognoses. Multidisciplinary planning, especially in palliative cases, can reduce such waste.
Less frequent but serious return causes included “Mistakes in Request” and “Blood Group Mismatch.” Although rare, they indicate critical protocol failures. Preventing these errors requires comprehensive staff training, system-based safeguards such as LIS alerts, and double-checking mechanisms (4).
To address these challenges, hospital-wide digital interventions are essential. Tools such as transfusion order alerts, mandatory return documentation, and real-time dashboards can enhance accountability. Assigning clear responsibility for each transfusion order, alongside regular audits, promotes compliance and reduces waste.
Our findings also provide a valuable perspective on blood product management within Iran, revealing significant regional variation. The overall return percentage in our hospital, which fluctuated between 1.1% and 1.5%, compares very favorably with other published reports. For instance, a study in Qazvin province hospitals found an average wastage rate of 9.8% for all blood products, with packed red cell wastage in individual hospitals ranging from 1.93% to as high as 30.7% (20). This contrasts sharply with our results, as does an earlier report from Kerman province, which also noted alarmingly high return rates of up to 25% for certain products (2). The significant difference suggests that although our institution has its own inefficiencies, its baseline blood management protocols may be more effective than those in other domestic centers. This highlights considerable variability in transfusion practices across the country and underscores the urgent need for standardized, national-level guidelines to reduce waste.
These challenges related to variability and inefficiency are not unique to Iran; similar studies in other teaching hospitals worldwide have also linked higher wastage to inexperience among trainees and the absence of real-time data tracking or feedback. For example, Taichung Tzu-Chi Hospital in Taiwan-an academic medical center-found that a significant portion of wastage was caused by excessive or inappropriate orders and staff unfamiliarity with transfusion procedures, emphasizing the need for better education and monitoring systems (15). Similarly, UCSF-affiliated hospitals in the U.S. reduced inefficiencies by using web-based dashboards to monitor blood inventory and cooler status in real time (21). Our findings also identify platelets and plasma as the most frequently wasted products. At the University of Maryland Medical Center, R-based dashboards enabled rapid adjustments in transfusion volumes during COVID-19 (4). In contrast, our retrospective, manual approach lacks predictive tools and real-time oversight.
Emerging technologies such as artificial intelligence (AI) and machine learning present promising solutions. These tools can forecast demand, flag high-risk return scenarios, and optimize inventory using historical and real-time data (22). Studies show that AI can improve the C/T ratio, reduce inventory needs, and lower wastage without affecting patient care (23,24). Predictive systems could even warn clinicians when an order is unlikely to be used, supporting smarter stewardship practices.
By delineating these issues in detail, we propose a foundation for strategic interventions that are both feasible and impactful. Key among these is the development of demand-prediction models based on statistical forecasting for plasma and platelets, moving beyond reliance on traditional MSBOS-style templates. Regular education and training on transfusion practices, with emphasis on the appropriate storage and handling of returned units, are also essential. Moreover, strengthening accountability through mandatory documentation and clear communication for each returned unit-alongside follow-up by transfusion medicine personnel-can help mitigate waste. To enhance oversight, we recommend implementing digital dashboards to monitor real-time blood usage trends and trigger audits in high-return departments. Finally, the adoption of predictive technologies such as AI and machine learning can assist in accurately forecasting product needs and guiding order volumes, particularly in smaller or resource-limited hospitals.
Moving forward, prospective studies and implementation trials will be essential to validate these strategies and support their integration into hospital-wide blood management programs. Strengthening transfusion accountability, particularly within educational institutions, has the potential to significantly reduce blood product wastage while improving patient care and safety.
Conclusion
Although progress has been made in reducing total returns at Imam Reza Hospital, significant challenges remain, particularly due to its educational environment, lack of digital tools, and frequent misuse or mishandling of returned products. Unlike centers that employ real-time analytics and AI-based forecasting, our institution relies on delayed manual audits. Future efforts must focus on minimizing both the rate and risk of returns by integrating technology, standardizing protocols, and fostering a culture of accountability. With these changes, we can better preserve our limited blood resources and improve patient safety.
Acknowledgement
The authors would like to thank Mr. Rasoul Zare for data collection assistance.
Funding Sources
This study was supported by Mashhad University of Medical Sciences.
Ethical Statement
The study protocol was approved by the Ethics Committee of Mashhad University of Medical Sciences (Approval code = IR.MUMS.IRH.REC.1403.244).
Conflicts of Interest
The authors declared no conflict of interest.
Author Contributions
All authors contributed to the study design, data analysis, and interpretation. All authors participated in drafting and writing the manuscript. Parsa Sheybani and Ata Nazarzadeh contributed equally as first authors. All authors read and approved the final manuscript.
Data Availability Statement
The data that support the findings of this study are available from the corresponding author upon reasonable request. The data are not publicly available due to ethical restrictions and patient privacy regulations.
Use of Artificial Intelligence
As the authors are non-native English speakers, Gemini (Google) was used during the preparation of this manuscript solely to assist with language editing, text structuring, and formatting to improve readability.
The AI tool was not used for systematic search strategies, data extraction, statistical analysis, or the generation of scientific conclusions. Following the use of this tool, all authors thoroughly reviewed, edited, and validated the content, and assume full responsibility for the accuracy, originality, and integrity of the final published article.
Research Article: Research Article |
Subject:
Laboratory hematology
Received: 2025/08/29 | Accepted: 2026/02/7 | Published: 2026/06/20 | ePublished: 2026/06/20
Received: 2025/08/29 | Accepted: 2026/02/7 | Published: 2026/06/20 | ePublished: 2026/06/20
References
1. Park M, Hur M, Kim H, Oh K, Kim H, Song YH, et al. Questionnaire survey on current red blood cell transport and storage in Korea for reducing wastage. Ann Lab Med. 2022;42(3):342-51. [View at Publisher] [DOI] [PMID] [Google Scholar]
2. Anani H, Baluchi I, Ghazizadeh M, Valandani HM, Khalilabadi RM. Evaluating the effect of tariff on wastage and return of blood products in Kerman province. Transfus Clin Biol. 2018;25(1):44-8. [View at Publisher] [DOI] [PMID] [Google Scholar]
3. Yazer MH, Deandrade DS, Triulzi DJ, Wisniewski MK, Waters JH. Electronic enhancements to blood ordering reduce component waste. Transfusion. 2016;56(3):564-70. [View at Publisher] [DOI] [PMID] [Google Scholar]
4. Murphy C, Jackson B, Fontaine M. Tools for rapid analysis of blood usage and inventory during the COVID ‐19 pandemic. Transfusion. 2020;60(10):2199-202. [View at Publisher] [DOI] [PMID] [Google Scholar]
5. Park M, Hur M, Yi A, Kim H, Lee HK, Jeon EY, et al. Utility of temperature‐sensitive indicators for temperature monitoring of red‐blood‐cell units. Vox Sang. 2019;114(5):487-94. [View at Publisher] [DOI] [PMID] [Google Scholar]
6. Gallagher T, Darby S, Vodanovich M, Campbell L, Tovey J. Patient blood management nurse vs transfusion nurse: is it time to merge? Br J Nurs. 2015;24(9):492-5. [View at Publisher] [DOI] [PMID] [Google Scholar]
7. Aplin K, Pitt T, Allen J, Roy A, Tidey K, Ball J, et al. Extending the 30‐minute rule for red cell units - investigation of the bacterial risk of 60‐minute exposures to ambient temperature. Vox Sang. 2019;114(3):189-97. [View at Publisher] [DOI] [PMID] [Google Scholar]
8. Devine DV, Serrano K. The platelet storage lesion. Clin Lab Med. 2010;30(2):475-87. [View at Publisher] [DOI] [PMID] [Google Scholar]
9. Wu DW, Friedman MT, Lombardi DP, Hwang R, Sender J, Cobaj V, et al. Impact of patient blood management on red blood cell utilization in an urban community teaching hospital: A seven-year retrospective study. Life (Basel). 2024;14(2):232. [View at Publisher] [DOI] [PMID] [Google Scholar]
10. Frank SM, Thakkar RN, Podlasek SJ, Ken Lee KH, Wintermeyer TL, Yang WW, et al. Implementing a health system-wide patient blood management program with a clinical community approach. Anesthesiology. 2017;127(5):754-64. [View at Publisher] [DOI] [PMID] [Google Scholar]
11. Gammon RR, Coberly E, Dubey R, Jindal A, Nalezinski S, Varisco JL. Patient blood management-It is about transfusing blood appropriately. Ann Blood. 2022;7:21. [View at Publisher] [DOI] [Google Scholar]
12. Carson JL, Guyatt G, Heddle NM, Grossman BJ, Cohn CS, Fung MK, et al. Clinical practice guidelines from the AABB: red blood cell transfusion thresholds and storage. JAMA. 2016;316(19):2025-35. [View at Publisher] [DOI] [PMID] [Google Scholar]
13. Saluja K, Thakral B, Marwaha N, Sharma RR. Platelet audit: Assessment and utilization of this precious resource from a tertiary care hospital. Asian J Transfus Sci. 2007;1(1):8-11. [View at Publisher] [DOI] [PMID] [Google Scholar]
14. Joon V, Robins RD, A HH, Kumar S, James S. Evaluating the crossmatch-to-transfusion ratio as a tool for analyzing and optimizing blood bank resource utilization: a retrospective observational study. Cureus. 2024;16(9):e69862. [View at Publisher] [DOI] [PMID] [Google Scholar]
15. Chien J-H, Yao C-Y, Chen H-F, Ho T-F. Trends in blood transfusion and causes of blood wastage: a retrospective analysis in a teaching hospital. BMC Health Serv Res. 2025;25(1):67. [View at Publisher] [DOI] [PMID] [Google Scholar]
16. Murphy S, Gardner FH. Platelet storage at 22 C; metabolic, morphologic, and functional studies. J Clin Invest. 1971;50(2):370-7. [View at Publisher] [DOI] [PMID] [Google Scholar]
17. Harmening DM. Modern blood banking & transfusion practices. 7th ed. Philadelphia: F.A. Davis Company;2018. [View at Publisher] [Google Scholar]
18. Slichter SJ, Corson J, Jones MK, Christoffel T, Pellham E, Bailey SL, et al. Exploratory studies of extended storage of apheresis platelets in a platelet additive solution (PAS). Blood. 2014;123(2):271-80. [View at Publisher] [DOI] [PMID] [Google Scholar]
19. Hoffmeister KM, Felbinger TW, Falet H, Denis CV, Bergmeier W, Mayadas TN, et al. The clearance mechanism of chilled blood platelets. Cell. 2003;112(1):87-97. [View at Publisher] [DOI] [PMID] [Google Scholar]
20. Far RM, Rad FS, Abdolazimi Z, Daneshi Kohan MM. Determination of rate and causes of wastage of blood and blood products in Iranian hospitals. Turk J Haematol. 2014;31(2):161-7. [View at Publisher] [DOI] [PMID] [Google Scholar]
21. Woo JS, Suslow P, Thorsen R, Ma R, Bakhtary S, Moayeri M, et al. Development and implementation of real-time web-based dashboards in a multisite transfusion service. J Pathol Inform. 2019:10:3. [View at Publisher] [DOI] [PMID] [Google Scholar]
22. Kwon HJ, Park S, Park YH, Baik SM, Park DJ. Development of blood demand prediction model using artificial intelligence based on national public big data. Digit Health. 2024;10:20552076231224245. [View at Publisher] [DOI] [PMID] [Google Scholar]
23. Thakur SK, Sinha AK, Negi DK, Singh S. Forecasting demand for blood products: Towards inventory management of a perishable product. Bioinformation. 2024;20(1):20-8. [View at Publisher] [DOI] [PMID] [Google Scholar]
24. Farrington J, Alimam S, Utley M, Li K, Wong WK. Many happy returns: machine learning to support platelet issuing and waste reduction in hospital blood banks. arXiv [Preprint]. 2024. [View at Publisher] [DOI] [Google Scholar]
Send email to the article author
| Rights and permissions | |
 |
This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License. |

This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License.
Contact us
Tel & Fax: (+98) 17-32450093
E-mail:
 goums.ac.ir
 yahoo.com