
Tue, Sep 22, 2026

Volume 20, Issue 3 (May-Jun 2026)
mljgoums 2026, 20(3): 38-41 |
Back to browse issues page



Download citation:
BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:


BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:
Nasirzadeh Z, Shafighi S T. Metallo-β-lactamase detection in imipenem-resistant Acinetobacter spp. and Pseudomonas aeruginosa: A combined phenotypic and molecular study. mljgoums 2026; 20 (3) :38-41
URL: http://mlj.goums.ac.ir/article-1-1855-en.html
URL: http://mlj.goums.ac.ir/article-1-1855-en.html


1- Department of Biology, Ra.C., Islamic Azad University, Rasht, Iran , zahranasirzade94@gmail.com
2- Department of Biology, Ra.C., Islamic Azad University, Rasht, Iran
2- Department of Biology, Ra.C., Islamic Azad University, Rasht, Iran
Full-Text [PDF 453 kb]
(1688 Downloads)
| Abstract (HTML) (6332 Views)
Discussion
The clinical utility of carbapenems has been compromised by the emergence of carbapenemase-producing bacterial strains, primarily Metallo-β-lactamases, thus undermining their role as reserve drugs (23). Carbapenem resistance is primarily observed in Gram-negative bacteria, such as P. aeruginosa and Acinetobacter species (24), and may arise either intrinsically or through transferable carbapenemase-encoding genes (25). Patients infected with carbapenem-resistant pathogens experience higher mortality than those infected with carbapenem-sensitive organisms (26).
In this study, P. aeruginosa showed high resistance to cefotaxime and piperacillin (84% and 52%, respectively), while Acinetobacter spp. displayed elevated resistance to all tested antibiotics except imipenem. These results align with previous reports by Fallah et al. regarding the resistance of Acinetobacter (27). Similar rates of resistance in Acinetobacter, as observed in our study, were also reported by Namaei et al. (28). Furthermore, Moosavian et al. reported that clinical P. aeruginosa isolates exhibited high resistance to ceftazidime, consistent with the results of the present study (29).
The trend observed in these studies indicates fluctuations in antibiotic resistance rates. The causes of these variations may include differences in resistance across regions, infection type, sample size, and the antibiotics used in disk assays. High antibiotic pressure, resulting from increased empirical or excessive use of antibiotics, seems to play a role in the emergence of carbapenem resistance among hospital isolates.
Higher rates of antimicrobial resistance were observed in Acinetobacter than in P. aeruginosa in the present study. Additionally, a significant percentage of clinical P. aeruginosa isolates exhibited intermediate susceptibility to antibiotics, indicating a potential need for further research into the resistance patterns of these isolates in the future.
The rise and global distribution of metallo-β-lactamases (MBLs), a leading mechanism of carbapenem resistance, represent a significant threat to healthcare systems. This threat stems not only from their capacity to confer high-level resistance but also from the presence of highly mobile genetic elements in genes such as blaIMP and blaVIM (30). Consequently, another aim of this research was to identify MBL-producing samples and the blaIMP and blaVIM genes in clinical P. aeruginosa and Acinetobacter spp. isolates.
In 2018, Subramaniyan et al. utilized the E-strip test method to identify MBL producers and the PCR method to detect the bla gene. They stated that 26.1% of MBL producers were P. aeruginosa, while 25% were Acinetobacter. The blaVIM gene, which encodes metallo-β-lactamase, was identified in 26% of P. aeruginosa, whereas the blaIMP gene was absent in P. aeruginosa. In Acinetobacter, the metallo-β-lactamase-producing gene, including the blaVIM gene, was reported in 4.4% of the strains, and the blaIMP gene in 5.2% (31). These results differ from those of the present study, showing a much higher abundance of metallo-β-lactamase-producing genes in native strains, possibly due to differences in the horizontal transfer of resistance genes.
In the study by Namai et al. in 2021, MBL production was observed in 40% of P. aeruginosa and 93.3% of Acinetobacter. It was found that 33.3% and 46.7% of P. aeruginosa isolates were resistant to carbapenems, and 13.3% and 28.9% of carbapenem-resistant Acinetobacter harbored the blaIMP-1 and blaVIM-1 genes, respectively (28). The results of that research showed a higher frequency of MBL compared to the current research, but the abundance of blaIMP and blaVIM genes was somewhat similar to the current study.
In an earlier study by Tarashi et al., the presence of blaIMP-1 and blaVIM-1 genes was observed in 30 (16.8%) and 52 (29.2%) strains of P. aeruginosa, respectively. The blaIMP-1 and blaVIM-1 genes were detected in 10 (5.3%) and 34 (18.18%) Acinetobacter isolates, respectively (32). The results of this study are close to those of the present study, with the difference being the lower reported frequency of the blaVIM gene in Acinetobacter.
Conclusion
The results of this research carry significant implications for both clinical practice and public health. Rapid identification and tracking of clinical isolates of P. aeruginosa and Acinetobacter producing metallo-beta-lactamase enzymes are crucial for tailoring effective treatment strategies and inhibiting the transmission of multidrug-resistant infections in healthcare environments. Resistance to carbapenems is primarily caused by the presence of metallo-beta-lactamase-producing genes, although non-enzymatic factors may also play a role. The increasing prevalence of carbapenem-resistant strains underscores the need for continuous monitoring and surveillance, as well as the implementation of rapid diagnostic tests to guide therapy. From a public health perspective, the results highlight the urgent need for comprehensive infection control programs and antimicrobial stewardship policies to combat the growing threat of antimicrobial resistance. Furthermore, global efforts are needed to reduce the misuse of antibiotics and promote responsible prescribing practices to slow the spread of resistance in healthcare settings.
Acknowledgement
The present article originates from an MSc thesis and was funded by the Islamic Azad University of Rasht, Iran.
Funding Sources
The authors received no financial support for the research, authorship, and/or publication of this article.
Ethical Statement
Not applicable since the study did not involve human or animal subjects.
Conflicts of Interest
The authors declare no conflict of interest.
Author Contributions
All authors were involved in study design, data collection, article approval, and statistical analysis.
Data Availability Statement
The data supporting this study are available from the corresponding author upon reasonable request.
Use of Artificial Intelligence
The authors did not use artificial intelligence in any part of the research or manuscript preparation process.
Full-Text: (149 Views)
Introduction
The growing prevalence of antimicrobial resistance (AMR) poses a major challenge to public health in the 21st century (1-3). The incidence of multidrug-resistant Gram-negative bacterial infections has escalated significantly in every region of the world (4). Environmental pathogens, particularly nonfermentative Gram-negative species, including Pseudomonas aeruginosa (5) and Acinetobacter spp. (6,7), are now frequently implicated in healthcare-associated multidrug-resistant infections (8-10). The transfer of bacteria and genes between humans, animals, and the environment renders antibiotics increasingly ineffective, leading to infections that are more difficult to treat and higher rates of death (11).
Resistance to carbapenems, which serve as a critical final option in antibiotic therapy, has become a significant global issue. Carbapenems, along with penicillins and cephalosporins, are central to this problem, as they are hydrolyzed by metallo-beta-lactamases (MBLs) (12,13). Metallo-beta-lactamases are zinc-dependent hydrolases that inactivate almost all beta-lactam antibiotics. Gram-negative bacteria expressing MBLs have severely limited available therapeutic options. MBLs function by binding critical metal ions in the periplasm, but their activity diminishes when zinc is limited due to innate immune defenses (11-13). The activity of this enzyme group is susceptible to inhibition by substances including ethylenediaminetetraacetic acid (EDTA) and sodium mercaptoacetic acid (10,14).
Metallo-beta-lactamases are classified into different types based on their molecular structure, including IMP, VIM, NDM, SPM, GIM, SIM, DIM, KHM, TMB, FIM, and AIM. IMPs and VIMs represent the most frequently encountered MBLs, with production largely observed in Enterobacteriaceae and Gram-negative nonfermentative bacteria such as P. aeruginosa and Acinetobacter spp. Beta-lactamase-producing strains pose a significant risk in medical centers due to their ability to transfer genes to other bacteria and their tendency for long-term colonization in hospitals (15-17).
In the MENA region, carbapenem-resistant Acinetobacter isolates, often producing carbapenemases, are prevalent in hospitals and contribute to multidrug resistance, posing a significant threat in healthcare-associated infections (18). Similarly, P. aeruginosa strains carrying metallo-beta-lactamases (MBLs), such as VIM-2, VIM-5, and NDM-1, are widespread across countries such as Saudi Arabia, Iran, Tunisia, and Algeria. These resistance mechanisms, particularly VIM-2 and NDM-1, are commonly found in MBL-positive strains, underscoring the escalating difficulty of managing infections caused by these resistant bacteria in the region (19).
The antibiotic resistance of P. aeruginosa and Acinetobacter, which are significant causes of clinical cases in hospitals, to effective antibiotics such as imipenem is a critical concern (20,21). Prior research has examined the distribution of MBL genes in these pathogens across various Iranian provinces. In this research, we simultaneously investigated the frequency of imipenem-resistant P. aeruginosa and Acinetobacter isolates from Rasht, along with the presence of metallo-beta-lactamase-producing genes in these isolates. Finally, we compared the results obtained from phenotypic and genotypic studies.
Methods
This descriptive cross-sectional study involved the collection of 52 Acinetobacter and 25 P. aeruginosa isolates from clinical specimens previously identified in the microbiology laboratories of Razi University Hospital, Poursina Medical and Educational Center, Al-Zahra Maternity, and Rasool Akram Hospital in Rasht over a one-year period (June 2021 - June 2022). All Acinetobacter and P. aeruginosa isolates were sent to the laboratory at the Institute of Microbiology, Department of Biology, Islamic Azad University in Rasht for further investigation. The isolates were then examined at the Microbiology Laboratory of Azad University, Rasht. Identification and confirmation of the isolates were performed according to the Clinical & Laboratory Standards Institute (CLSI) guidelines.
Samples were cultured on MacConkey agar and incubated at 37°C for 24 hours. Identification of bacterial isolates was accomplished using conventional biochemical tests, including catalase, oxidase, triple-sugar-iron (TSI) agar, oxidation/fermentation of glucose using oF media, and growth at 42°C.
Metallo-β-lactamase-producing strains were screened using the combination disk diffusion test (CDDT) to determine their prevalence among the isolates (22). Imipenem (IMP) and a combination of IMP with ethylenediaminetetraacetic acid (EDTA), an MBL inhibitor, were applied to identify MBL-producing strains among imipenem-non-susceptible isolates.
A solution of 0.5 M EDTA was freshly prepared. Using a 0.5 McFarland standard, a lawn culture of the isolate was prepared on Mueller-Hinton agar. The imipenem disk and imipenem plus EDTA (0.5 M and 5 μl) were placed at least 4 cm apart. The test was considered positive when the imipenem + EDTA disk produced an inhibition zone more than 5 mm larger than that of imipenem alone after overnight incubation.
Total DNA from the bacterial isolates was isolated using the SinaPure EX6011 DNA extraction kit.
All imipenem-non-susceptible strains were screened by PCR for the blaVIM and blaIMP-1 genes using gene-specific primers. PCR amplification was carried out using VIM-F (5′-TTTGGTCGCATATCGCAACG-3′) and VIM-R (5′-CCATTCAGCCAGATCGGCAT-3′) for blaVIM, and IMP-F (5′-CTACCGCAGCAGAGTCTTTG-3′) and IMP-R (5′-AACCAGTTTTGCCTTACCAT-3′) for blaIMP. The PCR conditions were as follows: initial denaturation at 94°C for 5 min, followed by 30 cycles of 94°C for 1 min, annealing at 50°C for 1 min for blaVIM and 40°C for 1 min for blaIMP, and extension at 72°C for 1 min, with a final extension at 72°C for 10 min.
Following electrophoresis of PCR products on a 1% agarose gel in 1× TBE containing ethidium bromide at 120 V for 45 minutes, the resulting bands were examined under UV light with a transilluminator.
Results
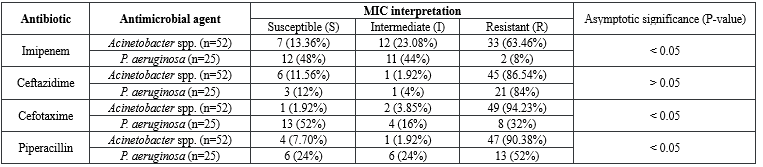
In the current research, we observed that Acinetobacter showed the highest susceptibility to imipenem (13.46%), whereas 94.2% were resistant to cefotaxime. In contrast, P. aeruginosa exhibited the highest resistance to ceftazidime (84%) and the greatest susceptibility to cefotaxime (52%).
Both P. aeruginosa and Acinetobacter spp. isolates displayed substantial resistance to ceftazidime, with resistance rates exceeding 80% in most cases.
The resistance patterns to imipenem, cefotaxime, and piperacillin showed a significant difference between P. aeruginosa and Acinetobacter isolates (p < 0.05). Antibiotic resistance patterns of P. aeruginosa and Acinetobacter spp. against the other groups of antibiotics are shown in Table 1.
Phenotypic screening of MBLs via the Combination Disk Diffusion Test (CDDT)
In our analysis, among the 25 clinical isolates of P. aeruginosa, 13 strains were imipenem-non-susceptible, and 2 (15.38%) were determined to be MBL producers by the CDDT. Additionally, of the 52 Acinetobacter strains, 45 isolates were imipenem resistant, and 18 (40%) were MBL producers.
In Figure 1, the combined disk test (CDT) shows an enhanced inhibition zone of >5 mm around the IPM + EDTA disk, indicating MBL positivity in clinical samples of Acinetobacter spp. and P. aeruginosa.
Identification of Metallo-β-lactamase genes
PCR analysis showed that the blaIMP and blaVIM genes were found in 7 (13.46%) and 11 (21.15%) isolated strains of Acinetobacter, respectively. The blaIMP and blaVIM genes were identified in 8 (32%) and 5 (20%) of 25 P. aeruginosa isolates, respectively.
The growing prevalence of antimicrobial resistance (AMR) poses a major challenge to public health in the 21st century (1-3). The incidence of multidrug-resistant Gram-negative bacterial infections has escalated significantly in every region of the world (4). Environmental pathogens, particularly nonfermentative Gram-negative species, including Pseudomonas aeruginosa (5) and Acinetobacter spp. (6,7), are now frequently implicated in healthcare-associated multidrug-resistant infections (8-10). The transfer of bacteria and genes between humans, animals, and the environment renders antibiotics increasingly ineffective, leading to infections that are more difficult to treat and higher rates of death (11).
Resistance to carbapenems, which serve as a critical final option in antibiotic therapy, has become a significant global issue. Carbapenems, along with penicillins and cephalosporins, are central to this problem, as they are hydrolyzed by metallo-beta-lactamases (MBLs) (12,13). Metallo-beta-lactamases are zinc-dependent hydrolases that inactivate almost all beta-lactam antibiotics. Gram-negative bacteria expressing MBLs have severely limited available therapeutic options. MBLs function by binding critical metal ions in the periplasm, but their activity diminishes when zinc is limited due to innate immune defenses (11-13). The activity of this enzyme group is susceptible to inhibition by substances including ethylenediaminetetraacetic acid (EDTA) and sodium mercaptoacetic acid (10,14).
Metallo-beta-lactamases are classified into different types based on their molecular structure, including IMP, VIM, NDM, SPM, GIM, SIM, DIM, KHM, TMB, FIM, and AIM. IMPs and VIMs represent the most frequently encountered MBLs, with production largely observed in Enterobacteriaceae and Gram-negative nonfermentative bacteria such as P. aeruginosa and Acinetobacter spp. Beta-lactamase-producing strains pose a significant risk in medical centers due to their ability to transfer genes to other bacteria and their tendency for long-term colonization in hospitals (15-17).
In the MENA region, carbapenem-resistant Acinetobacter isolates, often producing carbapenemases, are prevalent in hospitals and contribute to multidrug resistance, posing a significant threat in healthcare-associated infections (18). Similarly, P. aeruginosa strains carrying metallo-beta-lactamases (MBLs), such as VIM-2, VIM-5, and NDM-1, are widespread across countries such as Saudi Arabia, Iran, Tunisia, and Algeria. These resistance mechanisms, particularly VIM-2 and NDM-1, are commonly found in MBL-positive strains, underscoring the escalating difficulty of managing infections caused by these resistant bacteria in the region (19).
The antibiotic resistance of P. aeruginosa and Acinetobacter, which are significant causes of clinical cases in hospitals, to effective antibiotics such as imipenem is a critical concern (20,21). Prior research has examined the distribution of MBL genes in these pathogens across various Iranian provinces. In this research, we simultaneously investigated the frequency of imipenem-resistant P. aeruginosa and Acinetobacter isolates from Rasht, along with the presence of metallo-beta-lactamase-producing genes in these isolates. Finally, we compared the results obtained from phenotypic and genotypic studies.
Methods
This descriptive cross-sectional study involved the collection of 52 Acinetobacter and 25 P. aeruginosa isolates from clinical specimens previously identified in the microbiology laboratories of Razi University Hospital, Poursina Medical and Educational Center, Al-Zahra Maternity, and Rasool Akram Hospital in Rasht over a one-year period (June 2021 - June 2022). All Acinetobacter and P. aeruginosa isolates were sent to the laboratory at the Institute of Microbiology, Department of Biology, Islamic Azad University in Rasht for further investigation. The isolates were then examined at the Microbiology Laboratory of Azad University, Rasht. Identification and confirmation of the isolates were performed according to the Clinical & Laboratory Standards Institute (CLSI) guidelines.
Samples were cultured on MacConkey agar and incubated at 37°C for 24 hours. Identification of bacterial isolates was accomplished using conventional biochemical tests, including catalase, oxidase, triple-sugar-iron (TSI) agar, oxidation/fermentation of glucose using oF media, and growth at 42°C.
Metallo-β-lactamase-producing strains were screened using the combination disk diffusion test (CDDT) to determine their prevalence among the isolates (22). Imipenem (IMP) and a combination of IMP with ethylenediaminetetraacetic acid (EDTA), an MBL inhibitor, were applied to identify MBL-producing strains among imipenem-non-susceptible isolates.
A solution of 0.5 M EDTA was freshly prepared. Using a 0.5 McFarland standard, a lawn culture of the isolate was prepared on Mueller-Hinton agar. The imipenem disk and imipenem plus EDTA (0.5 M and 5 μl) were placed at least 4 cm apart. The test was considered positive when the imipenem + EDTA disk produced an inhibition zone more than 5 mm larger than that of imipenem alone after overnight incubation.
Total DNA from the bacterial isolates was isolated using the SinaPure EX6011 DNA extraction kit.
All imipenem-non-susceptible strains were screened by PCR for the blaVIM and blaIMP-1 genes using gene-specific primers. PCR amplification was carried out using VIM-F (5′-TTTGGTCGCATATCGCAACG-3′) and VIM-R (5′-CCATTCAGCCAGATCGGCAT-3′) for blaVIM, and IMP-F (5′-CTACCGCAGCAGAGTCTTTG-3′) and IMP-R (5′-AACCAGTTTTGCCTTACCAT-3′) for blaIMP. The PCR conditions were as follows: initial denaturation at 94°C for 5 min, followed by 30 cycles of 94°C for 1 min, annealing at 50°C for 1 min for blaVIM and 40°C for 1 min for blaIMP, and extension at 72°C for 1 min, with a final extension at 72°C for 10 min.
Following electrophoresis of PCR products on a 1% agarose gel in 1× TBE containing ethidium bromide at 120 V for 45 minutes, the resulting bands were examined under UV light with a transilluminator.
Results
In the current research, we observed that Acinetobacter showed the highest susceptibility to imipenem (13.46%), whereas 94.2% were resistant to cefotaxime. In contrast, P. aeruginosa exhibited the highest resistance to ceftazidime (84%) and the greatest susceptibility to cefotaxime (52%).
Both P. aeruginosa and Acinetobacter spp. isolates displayed substantial resistance to ceftazidime, with resistance rates exceeding 80% in most cases.
The resistance patterns to imipenem, cefotaxime, and piperacillin showed a significant difference between P. aeruginosa and Acinetobacter isolates (p < 0.05). Antibiotic resistance patterns of P. aeruginosa and Acinetobacter spp. against the other groups of antibiotics are shown in Table 1.
Phenotypic screening of MBLs via the Combination Disk Diffusion Test (CDDT)
In our analysis, among the 25 clinical isolates of P. aeruginosa, 13 strains were imipenem-non-susceptible, and 2 (15.38%) were determined to be MBL producers by the CDDT. Additionally, of the 52 Acinetobacter strains, 45 isolates were imipenem resistant, and 18 (40%) were MBL producers.
In Figure 1, the combined disk test (CDT) shows an enhanced inhibition zone of >5 mm around the IPM + EDTA disk, indicating MBL positivity in clinical samples of Acinetobacter spp. and P. aeruginosa.
Identification of Metallo-β-lactamase genes
PCR analysis showed that the blaIMP and blaVIM genes were found in 7 (13.46%) and 11 (21.15%) isolated strains of Acinetobacter, respectively. The blaIMP and blaVIM genes were identified in 8 (32%) and 5 (20%) of 25 P. aeruginosa isolates, respectively.
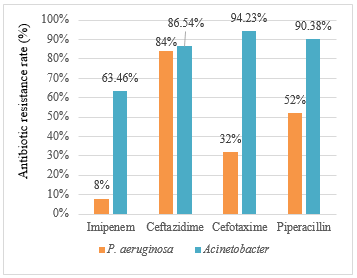
 Figure 2. Representative images of phenotypic detection of MBL production in A: Acinetobacter spp. (Positive control) and B: P. aeruginosa (Positive control). Imipenem: 10 µg/disk; EDTA: 0.5 µl/disk; ZOI: Zone of Inhibition. |
|
Table 1. Antimicrobial susceptibility results of Acinetobacter spp. and pseudomonas aeruginosa isolates
 |
Discussion
The clinical utility of carbapenems has been compromised by the emergence of carbapenemase-producing bacterial strains, primarily Metallo-β-lactamases, thus undermining their role as reserve drugs (23). Carbapenem resistance is primarily observed in Gram-negative bacteria, such as P. aeruginosa and Acinetobacter species (24), and may arise either intrinsically or through transferable carbapenemase-encoding genes (25). Patients infected with carbapenem-resistant pathogens experience higher mortality than those infected with carbapenem-sensitive organisms (26).
In this study, P. aeruginosa showed high resistance to cefotaxime and piperacillin (84% and 52%, respectively), while Acinetobacter spp. displayed elevated resistance to all tested antibiotics except imipenem. These results align with previous reports by Fallah et al. regarding the resistance of Acinetobacter (27). Similar rates of resistance in Acinetobacter, as observed in our study, were also reported by Namaei et al. (28). Furthermore, Moosavian et al. reported that clinical P. aeruginosa isolates exhibited high resistance to ceftazidime, consistent with the results of the present study (29).
The trend observed in these studies indicates fluctuations in antibiotic resistance rates. The causes of these variations may include differences in resistance across regions, infection type, sample size, and the antibiotics used in disk assays. High antibiotic pressure, resulting from increased empirical or excessive use of antibiotics, seems to play a role in the emergence of carbapenem resistance among hospital isolates.
Higher rates of antimicrobial resistance were observed in Acinetobacter than in P. aeruginosa in the present study. Additionally, a significant percentage of clinical P. aeruginosa isolates exhibited intermediate susceptibility to antibiotics, indicating a potential need for further research into the resistance patterns of these isolates in the future.
The rise and global distribution of metallo-β-lactamases (MBLs), a leading mechanism of carbapenem resistance, represent a significant threat to healthcare systems. This threat stems not only from their capacity to confer high-level resistance but also from the presence of highly mobile genetic elements in genes such as blaIMP and blaVIM (30). Consequently, another aim of this research was to identify MBL-producing samples and the blaIMP and blaVIM genes in clinical P. aeruginosa and Acinetobacter spp. isolates.
In 2018, Subramaniyan et al. utilized the E-strip test method to identify MBL producers and the PCR method to detect the bla gene. They stated that 26.1% of MBL producers were P. aeruginosa, while 25% were Acinetobacter. The blaVIM gene, which encodes metallo-β-lactamase, was identified in 26% of P. aeruginosa, whereas the blaIMP gene was absent in P. aeruginosa. In Acinetobacter, the metallo-β-lactamase-producing gene, including the blaVIM gene, was reported in 4.4% of the strains, and the blaIMP gene in 5.2% (31). These results differ from those of the present study, showing a much higher abundance of metallo-β-lactamase-producing genes in native strains, possibly due to differences in the horizontal transfer of resistance genes.
In the study by Namai et al. in 2021, MBL production was observed in 40% of P. aeruginosa and 93.3% of Acinetobacter. It was found that 33.3% and 46.7% of P. aeruginosa isolates were resistant to carbapenems, and 13.3% and 28.9% of carbapenem-resistant Acinetobacter harbored the blaIMP-1 and blaVIM-1 genes, respectively (28). The results of that research showed a higher frequency of MBL compared to the current research, but the abundance of blaIMP and blaVIM genes was somewhat similar to the current study.
In an earlier study by Tarashi et al., the presence of blaIMP-1 and blaVIM-1 genes was observed in 30 (16.8%) and 52 (29.2%) strains of P. aeruginosa, respectively. The blaIMP-1 and blaVIM-1 genes were detected in 10 (5.3%) and 34 (18.18%) Acinetobacter isolates, respectively (32). The results of this study are close to those of the present study, with the difference being the lower reported frequency of the blaVIM gene in Acinetobacter.
Conclusion
The results of this research carry significant implications for both clinical practice and public health. Rapid identification and tracking of clinical isolates of P. aeruginosa and Acinetobacter producing metallo-beta-lactamase enzymes are crucial for tailoring effective treatment strategies and inhibiting the transmission of multidrug-resistant infections in healthcare environments. Resistance to carbapenems is primarily caused by the presence of metallo-beta-lactamase-producing genes, although non-enzymatic factors may also play a role. The increasing prevalence of carbapenem-resistant strains underscores the need for continuous monitoring and surveillance, as well as the implementation of rapid diagnostic tests to guide therapy. From a public health perspective, the results highlight the urgent need for comprehensive infection control programs and antimicrobial stewardship policies to combat the growing threat of antimicrobial resistance. Furthermore, global efforts are needed to reduce the misuse of antibiotics and promote responsible prescribing practices to slow the spread of resistance in healthcare settings.
Acknowledgement
The present article originates from an MSc thesis and was funded by the Islamic Azad University of Rasht, Iran.
Funding Sources
The authors received no financial support for the research, authorship, and/or publication of this article.
Ethical Statement
Not applicable since the study did not involve human or animal subjects.
Conflicts of Interest
The authors declare no conflict of interest.
Author Contributions
All authors were involved in study design, data collection, article approval, and statistical analysis.
Data Availability Statement
The data supporting this study are available from the corresponding author upon reasonable request.
Use of Artificial Intelligence
The authors did not use artificial intelligence in any part of the research or manuscript preparation process.
Research Article: Research Article |
Subject:
Microbiology
Received: 2024/08/12 | Accepted: 2025/08/10 | Published: 2026/06/28 | ePublished: 2026/06/28
Received: 2024/08/12 | Accepted: 2025/08/10 | Published: 2026/06/28 | ePublished: 2026/06/28
References
1. Antimicrobial Resistance Collaborators. Global burden of bacterial antimicrobial resistance in 2019: a systematic analysis. Lancet. 2022;399(10325):629-55. [View at Publisher] [DOI] [PMID] [Google Scholar]
2. Mahmoodi F, Rezatofighi SE, Akhoond MR. Antimicrobial resistance and metallo-beta-lactamase producing among commensal Escherichia coli isolates from healthy children of Khuzestan and Fars provinces; Iran. BMC Microbiol. 2020;20(1):366. [View at Publisher] [DOI] [PMID] [Google Scholar]
3. Sartelli M, Weber DG, Ruppé E, Bassetti M, Wright BJ, Ansaloni L, et al. Antimicrobials: a global alliance for optimizing their rational use in intra-abdominal infections (AGORA). World Journal of Emergency Surgery. 2016;11(1):33. [View at Publisher] [DOI] [Google Scholar]
4. Dias VC, Resende JA, Bastos AN, De Andrade Bastos LQ, De Andrade Bastos VQ, Bastos RV, et al. Epidemiological, Physiological, and Molecular Characteristics of a Brazilian Collection of Carbapenem-Resistant Acinetobacter baumannii and P. aeruginosa . Microb Drug Resist. 2017;23(7):852-63. [View at Publisher] [DOI] [PMID] [Google Scholar]
5. Breidenstein EB, de la Fuente-Núñez C, Hancock RE. Pseudomonas aeruginosa: all roads lead to resistance. Trends Microbiol. 2011;19(8):419-26. [View at Publisher] [DOI] [PMID] [Google Scholar]
6. Peleg AY, Seifert H, Paterson DL. Acinetobacter baumannii: emergence of a successful pathogen. Clin Microbiol Rev. 2008;21(3):538-82. [View at Publisher] [DOI] [PMID] [Google Scholar]
7. Alsan M, Klompas M. Acinetobacter baumannii: An Emerging and Important Pathogen. J Clin Outcomes Manag. 2010;17(8):363-9. [View at Publisher] [PMID] [Google Scholar]
8. Gaynes R, Edwards JR. Overview of nosocomial infections caused by gram-negative bacilli. Clin Infect Dis. 2005;41(6):848-54. [View at Publisher] [DOI] [PMID] [Google Scholar]
9. Ehlenbach WJ, Curtis JR. Noninvasive ventilation for patients near the end of life: what do we know and what do we need to know? Crit Care Med. 2008;36(3):1003-4. [View at Publisher] [DOI] [PMID] [Google Scholar]
10. Lupo A, Haenni M, Madec J-Y. Antimicrobial Resistance in Acinetobacter spp. and Pseudomonas spp. Microbiol Spectr. 2018;6(3):10.1128/microbiolspec.arba-0007-2017. [View at Publisher] [DOI] [PMID] [Google Scholar]
11. Bahr G, González LJ, Vila AJ. Metallo-β-lactamases in the Age of Multidrug Resistance: From Structure and Mechanism to Evolution, Dissemination, and Inhibitor Design. Chem Rev. 2021;121(13):7957-8094. [View at Publisher] [DOI] [PMID] [Google Scholar]
12. Bahr G, González LJ, Vila AJ. Metallo-β-lactamases and a tug-of-war for the available zinc at the host-pathogen interface. Curr Opin Chem Biol. 2022;66:102103. [View at Publisher] [DOI] [PMID] [Google Scholar]
13. Jeon JH, Lee JH, Lee JJ, Park KS, Karim AM, Lee C-R, et al. Structural basis for carbapenem-hydrolyzing mechanisms of carbapenemases conferring antibiotic resistance. Int J Mol Sci. 2015;16(5):9654-92. [View at Publisher] [DOI] [PMID] [Google Scholar]
14. Manenzhe RI, Zar HJ, Nicol MP, Kaba M. The spread of carbapenemase-producing bacteria in Africa: a systematic review. J Antimicrob Chemother. 2015;70(1):23-40. [View at Publisher] [DOI] [PMID] [Google Scholar]
15. Nikibakhsh M, Firoozeh F, Badmasti F, Kabir K, Zibaei M. Molecular study of metallo-β-lactamases and integrons in Acinetobacter baumannii isolates from burn patients. BMC Infect Dis. 2021;21(1):782. [View at Publisher] [DOI] [PMID] [Google Scholar]
16. Ayoub Moubareck C, Hammoudi Halat D. Insights into Acinetobacter baumannii: A Review of Microbiological, Virulence, and Resistance Traits in a Threatening Nosocomial Pathogen. Antibiotics (Basel). 2020;9(3):119. [View at Publisher] [DOI] [PMID] [Google Scholar]
17. Queenan AM, Bush K. Carbapenemases: the versatile beta-lactamases. Clin Microbiol Rev. 2007;20(3):440-58, table of contents. [View at Publisher] [DOI] [PMID] [Google Scholar]
18. Dandachi I, Chaddad A, Hanna J, Matta J, Daoud Z. Understanding the Epidemiology of Multi-Drug Resistant Gram-Negative Bacilli in the Middle East Using a One Health Approach. Front Microbiol. 2019;10:1941. [View at Publisher] [DOI] [PMID] [Google Scholar]
19. Ghasemian A, Salimian Rizi K, Rajabi Vardanjani H, Nojoomi F. Prevalence of Clinically Isolated Metallo-beta-lactamase-producing P. aeruginosa , Coding Genes, and Possible Risk Factors in Iran. Iran J Pathol. 2018;13(1):1-9. [View at Publisher] [DOI] [PMID] [Google Scholar]
20. Lister PD, Wolter DJ, Hanson ND. Antibacterial-resistant P. aeruginosa : clinical impact and complex regulation of chromosomally encoded resistance mechanisms. Clin Microbiol Rev. 2009;22(4):582-610. [View at Publisher] [DOI] [PMID] [Google Scholar]
21. Almasaudi SB. Acinetobacter spp. as nosocomial pathogens: Epidemiology and resistance features. Saudi J Biol Sci. 2018;25(3):586-96. [View at Publisher] [DOI] [PMID] [Google Scholar]
22. Lee K, Lim YS, Yong D, Yum JH, Chong Y. Evaluation of the Hodge test and the imipenem-EDTA double-disk synergy test for differentiating metallo-beta-lactamase-producing isolates of Pseudomonas spp. and Acinetobacter spp. J Clin Microbiol. 2003;41(10):4623-9. [View at Publisher] [DOI] [PMID] [Google Scholar]
23. Papp-Wallace KM, Endimiani A, Taracila MA, Bonomo RA. Carbapenems: past, present, and future. Antimicrob Agents Chemother. 2011;55(11):4943-60. [View at Publisher] [DOI] [PMID] [Google Scholar]
24. Noori N, Vandyosefi J, Sabet F, Ashrafi S, Ghazvini K. Frequency of IMP-1 and VIM Genes among Metallo-beta-Lactamase Producing Acinetobacter spp. Isolated from Health Care Associated Infections inNortheast of Iran. J Med Bacteriol. 2015;2(3-4):11-6. [View at Publisher] [Google Scholar]
25. Meletis G. Carbapenem resistance: overview of the problem and future perspectives. Ther Adv Infect Dis. 2016;3(1):15-21. [View at Publisher] [DOI] [PMID] [Google Scholar]
26. Falagas ME, Tansarli GS, Karageorgopoulos DE, Vardakas KZ. Deaths attributable to carbapenem-resistant Enterobacteriaceae infections. Emerg Infect Dis. 2014;20(7):1170-5. [View at Publisher] [DOI] [PMID] [Google Scholar]
27. Fallah F, Noori M, Hashemi A, Goudarzi H, Karimi A, Erfanimanesh S, et al. Prevalence of bla NDM, bla PER, bla VEB, bla IMP, and bla VIM Genes among Acinetobacter baumannii Isolated from Two Hospitals of Tehran, Iran. Scientifica (Cairo). 2014;2014:245162. [View at Publisher] [DOI] [PMID] [Google Scholar]
28. Namaei MH, Yousefi M, Askari P, Roshanravan B, Hashemi A, Rezaei Y. High prevalence of multidrug-resistant non-fermentative Gram-negative bacilli harboring bla (IMP-1) and bla (VIM-1) metallo-beta-lactamase genes in Birjand, south-east Iran. Iran J Microbiol. 2021;13(4):470-9. [View at Publisher] [DOI] [PMID] [Google Scholar]
29. Moosavian M, Rahimzadeh M. Molecular detection of metallo-β-lactamase genes, bla IMP-1, bla VIM-2 and bla SPM-1 in imipenem resistant P. aeruginosa isolated from clinical specimens in teaching hospitals of Ahvaz, Iran. Iran J Microbiol. 2015;7(1):2-6. [View at Publisher] [PMID] [Google Scholar]
30. Aghamiri S, Amirmozafari N, Fallah Mehrabadi J, Fouladtan B, Samadi Kafil H. Antibiotic Resistance Pattern and Evaluation of Metallo-Beta Lactamase Genes Including bla- IMP and bla- VIM Types in P. aeruginosa Isolated from Patients in Tehran Hospitals. ISRN Microbiol. 2014;2014:941507. [View at Publisher] [DOI] [PMID] [Google Scholar]
31. Subramaniyan JS, Sundaram JM. Occurrence of bla genes encoding carbapenem-resistant P. aeruginosa and Acinetobacter baumannii from Intensive Care Unit in a tertiary care hospital. J Lab Physicians. 2018;10(2):208-13. [View at Publisher] [DOI] [PMID] [Google Scholar]
32. Tarashi S, Goudarzi H, Erfanimanesh S, Pormohammad A, Hashemi A. Phenotypic and Molecular Detection of Metallo-Beta-Lactamase Genes Among Imipenem Resistant P. aeruginosa and Acinetobacter baumannii Strains Isolated From Patients with Burn Injuries. Arch Clin Infect Dis. 2016;11(4):e39036. [View at Publisher] [DOI] [Google Scholar]
Send email to the article author
| Rights and permissions | |
 |
This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License. |

This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License.
Contact us
Tel & Fax: (+98) 17-32450093
E-mail:
 goums.ac.ir
 yahoo.com